
Congenital adrenal hyperplasia (21-hydroxylase deficiency)
On ABGC's listListed on the ABGC Self-Study GuideLog in to starLast updated Nov 4, 2026
A newborn female has ambiguous genitalia with clitoromegaly and labial fusion. She develops a salt-wasting crisis at 2 weeks of age with hyponatremia and hyperkalemia.
AR; CYP21A2, encoding steroid 21-hydroxylase. Most pathogenic alleles are deletions or gene conversions involving the neighboring pseudogene CYP21A1P.
- Most common cause of CAH (~95%)
Forms:
- Classic salt-wasting: Severe enzyme deficiency, cortisol + aldosterone deficiency
- Classic simple virilizing: Cortisol deficiency, aldosterone usually adequate
- Non-classic: Mild, late-onset (hirsutism, irregular menses)
21-hydroxylase is the adrenal cytochrome P450 enzyme on the pathways to cortisol and aldosterone. When it fails, the cortisol pathway is blocked and 17-hydroxyprogesterone (17-OHP) builds up; the excess is shunted into the intact androgen pathway, which virilizes a 46,XX fetus. Lack of cortisol weakens negative feedback on pituitary ACTH, so ACTH drives the adrenal cortex continuously into hyperplasia. The mineralocorticoid pathway needs only minimal 21-hydroxylase activity, which is why overt salt wasting is a feature of the most severe form, although some aldosterone deficiency is found in all forms.
CYP21A2 lies 30 kb from CYP21A1P, 98% identical in exons. Unequal crossing over gives a 30-kb deletion that leaves a nonfunctional chimeric gene (20% to 30% of alleles), and gene conversion copies inactivating pseudogene variants into CYP21A2. One conversion can put several variants on one allele, so testing both parents determines whether the variants lie on the same or separate alleles.
Residual activity groups alleles: null alleles (0%) usually give salt wasting, p.Ile173Asn (2% to 11%) usually simple virilizing, and p.Val282Leu or p.Pro31Leu (about 20% to 50%) non-classic. A direct genotype-phenotype correlation holds for only about half of genotypes; in non-classic disease the milder allele sets the phenotype.
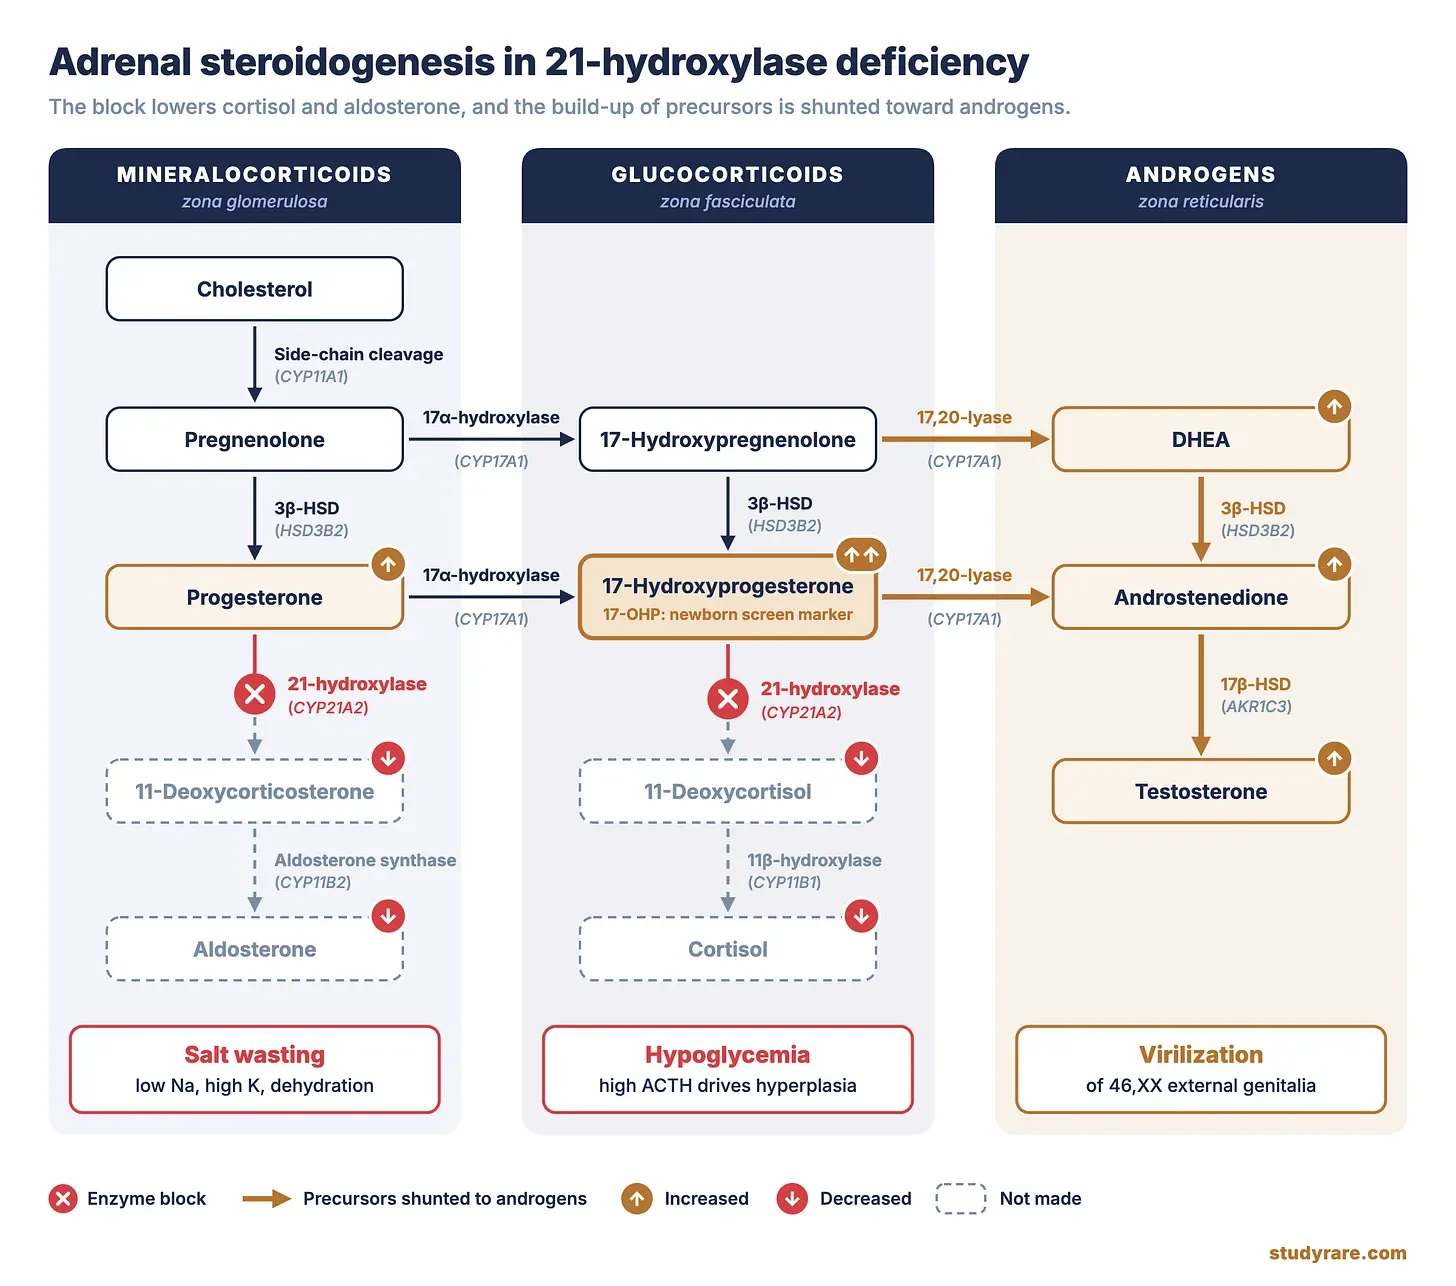
- Females: Virilization, ambiguous genitalia at birth
- Males: May appear normal at birth, precocious puberty later
- Salt-wasting: Hyponatremia, hyperkalemia, hypotension, shock
- Elevated 17-hydroxyprogesterone
Newborn Screening: On RUSP (elevated 17-OHP)
- Elevated 17-hydroxyprogesterone (17-OHP) is the key biochemical marker; included on newborn screening
- ACTH (cosyntropin) stimulation test confirms borderline or non-classic cases (exaggerated 17-OHP rise)
- CYP21A2 molecular testing confirms the diagnosis and guides carrier and prenatal counseling
- Salt-wasting form: hyponatremia, hyperkalemia, low aldosterone, elevated plasma renin
- Glucocorticoid and mineralocorticoid replacement